
Antidepressant Hair Loss: SSRIs and Thinning Explained
Learn how SSRIs and other antidepressants can cause hair thinning, what symptoms to watch for, diagnosis, treatment options, and whether a hair transplant helps
What Is Antidepressant-Related Hair Loss?
Antidepressant-related hair loss is a form of shedding or thinning that some people experience while taking medications for depression, anxiety, or other mood disorders. It's not a universal side effect, and it doesn't happen to everyone, but it's well-documented enough that dermatologists and psychiatrists recognize it as a real phenomenon. The most commonly implicated drugs are selective serotonin reuptake inhibitors (SSRIs), though other classes like serotonin-norepinephrine reuptake inhibitors (SNRIs), tricyclics, and even some atypical antidepressants have been linked to hair changes. The loss is usually diffuse — a general thinning across the scalp rather than distinct bald patches — and it often reverses once the medication is stopped, though that's not always a simple decision.
How SSRIs and Other Antidepressants Can Cause Thinning
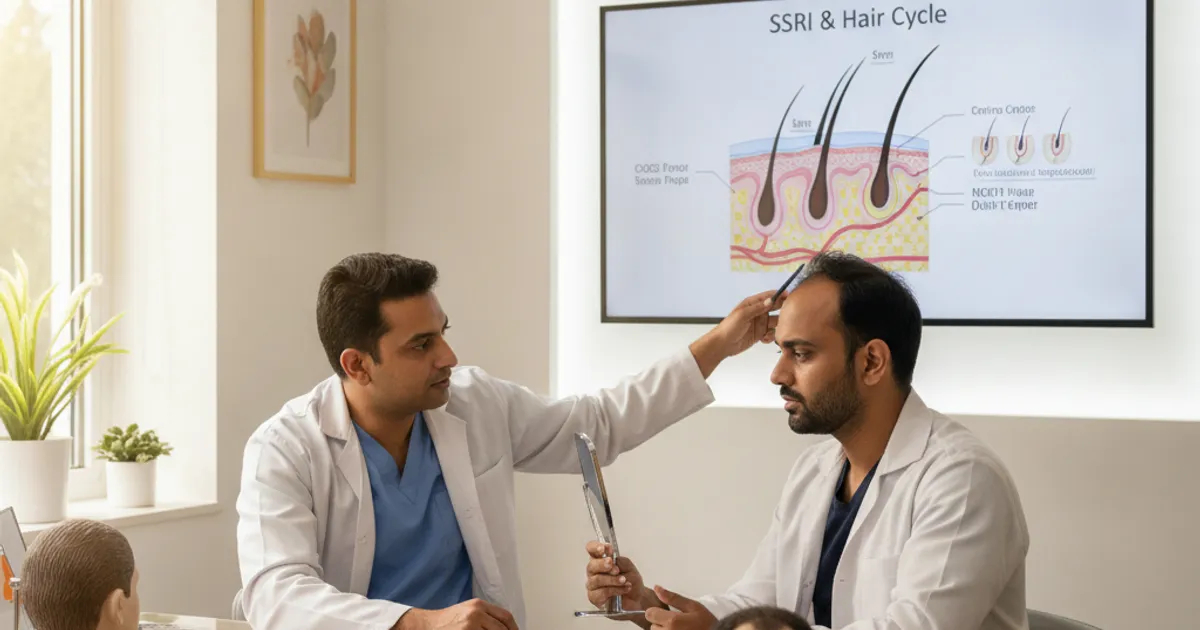
The exact mechanisms aren't fully understood, and research is still piecing together why some people shed hair on these drugs while others don't. Several theories exist, and they likely overlap. The most accepted explanation involves the hair growth cycle. Hair goes through phases: anagen (growth), catagen (transition), telogen (rest), and exogen (shedding). Many antidepressants appear to push more hairs than usual into the telogen phase prematurely, leading to a condition called telogen effluvium — a diffuse shedding that typically starts weeks to months after the trigger. Other proposed mechanisms include changes in blood flow to the follicle, nutritional interference (some antidepressants can affect appetite or nutrient absorption), and hormonal shifts. SSRIs specifically increase serotonin, which may influence prolactin levels and other hormones that play a role in hair cycling. There's also the possibility of an immune-mediated reaction in rare cases. It's worth noting that stress and depression itself can cause hair loss, so untangling cause and effect can be tricky.
- Telogen effluvium: premature shift of hair follicles into the resting phase, causing diffuse shedding.
- Hormonal changes: serotonin's effect on prolactin and other hormones may disrupt the hair cycle.
- Nutritional factors: appetite changes or gastrointestinal side effects could lead to mild nutrient deficiencies.
- Individual susceptibility: genetics and baseline hair health influence who experiences thinning.
- Dose and duration: higher doses and longer use may increase the likelihood, though any dose can trigger it.
Common Symptoms and Patterns to Look For
The hallmark of antidepressant-related hair loss is a gradual, diffuse thinning rather than receding hairlines or bald spots. You might notice more hair in your brush, on your pillow, or in the shower drain. The shedding is usually spread evenly across the scalp, though some people report more noticeable thinning at the temples or crown. It typically begins within the first few months of starting or increasing the dose of a medication, but it can also occur after months or even years of stable use. Unlike androgenetic alopecia (male or female pattern baldness), which follows a predictable pattern and is driven by genetics and hormones, medication-induced shedding tends to be more uniform. It's also important to distinguish from other causes like thyroid issues, iron deficiency, or stress-related telogen effluvium — a doctor can help sort that out.
- Increased shedding during washing or brushing (noticeably more than usual).
- Diffuse thinning across the entire scalp, not just the crown or hairline.
- Hair may feel thinner in texture or less voluminous.
- Onset typically weeks to months after starting or changing an antidepressant.
- No visible inflammation, scarring, or patchy bald spots (unless another condition is present).
| Feature | Antidepressant-Related Loss | Androgenetic Alopecia |
|---|---|---|
| Pattern | Diffuse, uniform thinning | Receding hairline, crown thinning |
| Onset | Weeks to months after medication start | Gradual over years |
| Reversibility | Often reversible after stopping | Progressive without treatment |
| Scalp appearance | Normal, no scarring | Normal, no scarring |
| Key trigger | Medication exposure | Genetics and hormones |
Diagnosing Antidepressant-Induced Hair Loss
Diagnosis is largely clinical and involves ruling out other causes. A dermatologist or trichologist will take a detailed history, including medication timeline, family history of hair loss, diet, stress levels, and any recent illnesses or surgeries. They'll examine the scalp for signs of inflammation, scarring, or patterned loss. Blood tests are commonly ordered to check ferritin (iron stores), thyroid function, vitamin D, and sometimes zinc and B12. A pull test — gently tugging a small section of hair — can help estimate shedding activity. In some cases, a scalp biopsy may be performed to rule out scarring alopecia or other conditions. The key diagnostic clue is the temporal relationship between starting the medication and the onset of shedding, and improvement after stopping the drug (if that's a safe option). It's important to work with both a dermatologist and the prescribing doctor, as stopping an antidepressant abruptly can cause withdrawal symptoms and mood destabilization.
- Detailed medication history: when the drug was started, dose changes, and other medications.
- Scalp examination to assess pattern and rule out scarring or inflammation.
- Blood tests: ferritin, thyroid panel, vitamin D, B12, zinc.
- Hair pull test to gauge active shedding.
- Biopsy in select cases to exclude other alopecias.
- Coordination with the prescribing psychiatrist or GP before any medication changes.
Treatment Options: From Topicals to PRP
Treatment depends on whether you can safely stop or switch the offending medication. If the antidepressant is essential and working well, the priority is managing the hair loss while staying on the drug. In many cases, the shedding stabilizes or improves over time even without stopping the medication, as the hair cycle adjusts. For persistent thinning, several evidence-based treatments can help. Topical minoxidil is the first-line option for diffuse thinning and is available over the counter in different strengths for men and women. Finasteride is only appropriate for male pattern baldness and is not typically used for medication-induced shedding unless there's coexisting androgenetic alopecia. Platelet-rich plasma (PRP) injections can stimulate follicles and are increasingly used for various types of hair loss, though evidence specific to antidepressant-induced shedding is limited. Low-level laser therapy and nutritional supplementation (if deficiencies are found) may also play a role. Always discuss with your doctor before adding treatments, as some can interact with psychiatric medications.
- Topical minoxidil: first-line for diffuse thinning; helps prolong the growth phase.
- Finasteride: only for male pattern baldness; not routinely used for medication-induced loss.
- PRP (platelet-rich plasma): injections that may stimulate follicle activity; evidence is growing but not definitive for this specific cause.
- Low-level laser therapy: may improve hair density in some cases.
- Nutritional correction: iron, vitamin D, zinc, and B12 if deficiencies are identified.
- Switching antidepressants: only under psychiatric guidance, as not all drugs cause hair loss equally.
| Treatment | Best For | Evidence Level | Notes |
|---|---|---|---|
| Minoxidil | Diffuse thinning | Strong for androgenetic alopecia; moderate for telogen effluvium | Over-the-counter; requires consistent use |
| Finasteride | Male pattern baldness | Strong for androgenetic alopecia | Not for women of childbearing age; not for medication-induced loss alone |
| PRP | Various hair loss types | Moderate; more studies needed | Clinic-based; multiple sessions |
| Low-level laser | Diffuse thinning | Moderate | At-home devices available |
| Nutritional supplements | Deficiency-related loss | Strong if deficiency present | Only after blood tests confirm need |
Is a Hair Transplant Suitable for Medication-Related Loss?
A hair transplant is generally not the first-line solution for antidepressant-related hair loss. The reason is simple: if the underlying cause is ongoing (i.e., you're still taking the medication and it's still triggering shedding), transplanted hair may not be immune to the same process. Hair transplants work best for stable, permanent hair loss — typically androgenetic alopecia where the donor area is resistant to DHT. In medication-induced telogen effluvium, the loss is often diffuse and temporary, and the donor area may also be affected. That said, if the shedding has stabilized and there's a clear diagnosis of coexisting pattern baldness, a transplant could be considered. But it's crucial to have realistic expectations and a thorough evaluation. A surgeon should confirm that the hair loss is stable and that the donor area is healthy. In many cases, treating the underlying cause and using medical therapy is more appropriate than surgery.
- Transplants are best for stable, permanent hair loss (e.g., androgenetic alopecia).
- Active medication-induced shedding should be resolved or stabilized first.
- Diffuse thinning may affect the donor area, reducing transplant viability.
- A thorough evaluation by a hair restoration surgeon is essential.
- Medical therapy (minoxidil, etc.) is usually tried before surgery.
What to Discuss With Your Doctor Before Stopping an Antidepressant
Stopping an antidepressant is not a decision to take lightly. The medication may be managing symptoms that are far more disruptive than hair thinning. Before making any changes, have an open conversation with your prescribing doctor. Bring up the hair loss specifically and ask whether it could be related to the medication. Discuss alternatives: sometimes switching to a different antidepressant with a lower risk of hair loss can help, but not all drugs are equal and what works for one person may not for another. Ask about the risks of discontinuation syndrome, which can include flu-like symptoms, insomnia, irritability, and mood swings. Also consider whether the hair loss might be caused by something else entirely — thyroid issues, iron deficiency, or stress. Your doctor may want to run tests or refer you to a dermatologist. The goal is to make an informed decision that balances mental health and hair health.
- Ask whether your specific medication is known to cause hair loss.
- Discuss the risks of stopping versus switching medications.
- Inquire about discontinuation syndrome and how to taper safely.
- Request blood tests to rule out other causes (ferritin, thyroid, vitamin D).
- Ask for a referral to a dermatologist if needed.
- Consider the impact of untreated depression or anxiety on overall health.
Frequently Asked Questions
Is hair loss from antidepressants permanent?
In most cases, it's temporary. Telogen effluvium typically resolves within several months after the trigger is removed, though it can take longer. If you continue the medication, the shedding may stabilize or persist. Permanent loss is more likely if there's coexisting androgenetic alopecia.
Which antidepressants are most likely to cause hair loss?
SSRIs like sertraline, fluoxetine, and paroxetine are commonly reported, but any antidepressant can potentially cause hair loss. Bupropion (Wellbutrin) is sometimes considered less likely, but individual reactions vary. There's no way to predict who will be affected.
Can I take minoxidil while on antidepressants?
Topical minoxidil is generally safe to use alongside antidepressants, as systemic absorption is minimal. However, always check with your doctor or pharmacist to rule out any interactions.
Should I stop my antidepressant to save my hair?
Never stop without medical advice. The risks of untreated depression or anxiety can be severe. Discuss alternatives with your doctor, such as dose adjustment, switching medications, or adding hair loss treatments.
Is a hair transplant a good idea for antidepressant-induced hair loss?
Usually not as a first step. Transplants are best for stable, permanent hair loss. If the shedding is active, surgery may not be appropriate. Wait until the condition stabilizes and consult a specialist.
How long after starting an antidepressant does hair loss begin?
It can vary widely, but many people notice shedding within the first few months after starting or increasing the dose, which aligns with the telogen phase of the hair cycle.
More Guides
- Hair Loss After Weight Loss Surgery: Timeline & Fixes
Hair loss after weight loss surgery is common. Learn the timeline, causes, treatments like minoxidil and PRP, and whether a hair transplant is right for you.
- Stress-Related Hair Loss: Recovery Time and Treatment
How long does stress-induced hair loss take to recover? Learn about telogen effluvium, diagnosis, treatments, and when a transplant may help.
- Female Hair Loss at the Back of the Head: Causes & Fixes
Learn why women lose hair at the back of the head, how it's diagnosed, and the best treatment options including minoxidil, PRP, and hair transplant suitability.
- Wellbutrin and Hair Loss: What You Need to Know
Learn how Wellbutrin may cause hair loss, how it's diagnosed, and what treatments—including hair transplant—can help you regrow hair.